


Progesterone Supplements (Oral and Vaginal)
Progesterone Supplements (Oral and Vaginal)
by Kris
* Please note that while I reference intramuscular progesterone injections, I don’t go into detail as I have no experience with them.
Why would you be taking progesterone supplements?
There are a few reasons you might be taking progesterone supplements, which can be delivered orally, through vaginal suppositories, or via intramuscular injection (commonly referred to as PIO). Some examples: (1) You have low progesterone levels. This is usually diagnosed by having a blood test done 7 days post-ovulation. (2) You have a short luteal phase regardless of the results of the 7 dpo progesterone results. I believe that any luteal phase less than 12 days is considered short. (3) Even if your progesterone level and luteal phase are fine, if you are doing IVF (and depending on the RE, IUI) you will probably be prescribed progesterone supplements. Taking the supplement just covers your bases.
Why would you take them orally or vaginally?
The oral supplement is definitely the least invasive way to do the job if it works for you. However, when you take progesterone (or apparently any hormone) orally, it must be metabolized by the liver, which makes the delivery system inefficient and less effective. As for vaginal supplements versus injections, all I can offer is what I’ve been told. For most women, there seems to be no difference in the results. My clinic uses the suppositories because they feel after all the pre-procedure injections they just don’t want to prescribe more injections. My RE also informed me that when they switched to suppositories their pregnancy rates increased. However, there does seem to be evidence that some women have a better response with the injections. I know there are women out in bloglandia who agree with this.
What to expect
You can expect to take the supplements until you take your beta. If it is negative, you will stop and your period will arrive. If it is positive, you will continue taking the supplements for at least a few more weeks and possibly through the entire first trimester. If you are having blood tests done after insemination or transfer and are using vaginal supplements, your blood tests may not reflect high progesterone levels. Do not freak out if your level seems low compared to your friend doing injections. The vaginal suppositories are not systemic- all the progesterone stays right around your uterus and does not show up in blood tests. That doesn’t mean it isn’t there. The common oral supplement is prometrium. If you are taking this, expect to feel tired… fast. Twenty minutes after taking this I was dead to the world. But I slept great.
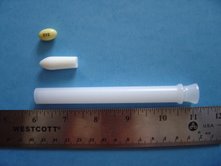
There are two vaginal forms: suppository (yellow pill–see picture) and suspended in gel (white bullet-like pill–see picture). The suppositories can be either prometrium (yes, the exact same pill you can take orally) or they can be pharmacy compounded. Not all pharmacies have the capabilities to compound these suppositories- at least not all American pharmacies. I have been told by my RE it doesn’t matter if you use prometrium or pharmacy compounded, but his preference is to use the pharmacy compounded. Whether you use prometrium or the compound suppositories, your dose will typically be 2 to 3 times per day. Expect to feel like you have constantly wet your pants. The prometrium is like a vitamin E–a softish gel capsule. In my experience, prometrium is much less oozy–one or two pantyliners a day should cover you just fine. You may notice some of the yellowish coating on your pantyliner. Gross, but normal. Prometrium can be kept at room temperature. The pharmacy compounded suppositories are very oozy. I frequently change panty liners when using these suppositories. These need to be kept cold or they will melt. When you take it out of the wrapper, it feels kind of waxy. But if you let it rest in your hand, the surface feels slick and oily. This is only the outer coating–if you look at the non-pointy end, you can see there is white goo inside the waxy shell. You may notice some of the disintegrated shell on your panty liner amongst the ooze. Also gross, but also normal.
The suspended in gel supplement (Crinone and similar products) comes in a pre-filled applicator (the pharmacy also gave me an applicator for taking the prometrium vaginally but I’ve never used it. I use my finger because it’s easier to wash.).
It’s been awhile, but as I recall, these applicators do not need to be kept cold. I don’t really remember any oozing, either. But I definitely remember this…when I read the insert, it said that I might see some of the suspension gel ooze out. I imagined that would be some sort of liquefied substance and I never saw any. Then one day I went to the bathroom and saw on my panties this disgusting glob of grainy cottage-cheesiness and I was horrified. That was a few days of the suspension gel–which doesn’t liquefy like I thought–finally succumbing to gravity. It was very gross and completely not what I expected, but also…normal. With all of these supplements, you may feel some bloating. They also cause me to have to pee a lot–especially in the middle of the night.
Problems you may encounter
Other than feeling like you are going to develop some sort of mold on your constantly moist naughty bits, there really aren’t too many problems. I have noticed that some time into the second week of the vaginal suppositories, my vagina feels irritated. If you’ve ever removed a tampon that was too dry, that’s what it feels like. Oh, and this (which I’m sorry, is painfully graphic)… I wiped front to back and when I first used the compounded suppositories and I noticed some irritation around my anus from the progesterone ooze that would linger behind when I was done. Now I just make sure I wipe the excess away from there–usually with damp tissue–and all sees to be well.
Personal Tips
As if the tush-wiping wasn’t personal. I try to make sure I space my dosages as evenly throughout the day as I can. And I try to lay down for as much of that as possible to allow the progesterone to absorb before oozing out. No one told me to do that…that’s just my neurosis. I have a three-a-day dose. I do one at 8 p.m. and then crawl into bed and read. I set my alarm for 4 a.m.- I usually have to pee around then anyway- and put in the next dose. At night, I fill a small glass with ice and just set the wrapped compounded suppository on top. This way I can keep the glass on my nightstand and avoid fumbling around my kitchen at 4 a.m. Then I go back to sleep for a few more hours. I take the third dose at noon and just deal with the instant ooze, since I’m at work. But if it’s a weekend, I think an afternoon nap is in order.
July 26, 2006 60 Comments
Semen Analysis
by Serenity
Why would you be doing a Semen Analysis (SA)?
Since male factor accounts for about 35% of infertility, a RE’s office will administer a SA as one of the first tests they’ll do to diagnose you as a couple.
A SA measures the following:
Volume (measured in mL)
Liquefaction time
Sperm count (both the overall count and per mL)
Sperm motility (the percentage of sperm that are moving – these are your “swimmers”). Most clinics also measure how many sperm are moving forward, which is called the “forward motility” test.
Morphology (the percentage of sperm that have a normal shape).
The SA also measures the pH balance, number of white blood cells, and amount of fructose in the sample.
What you can expect
Giving a sample
Generally, clinics require that you to not ejaculate for 48 hours before the test, BUT also do not abstain for more than 72 hours. In layman’s terms: they want you to ejaculate once between 2 and 3 days before the SA, but then abstain until after the SA.
Obviously, this is not a painful process, but it can be embarrassing. I have heard stories where someone’s husband had to use a bathroom off the waiting area to produce his sample – the poor guy! In most clinics, especially the bigger ones, though, they have a room set up with magazines (and even movies) for you to do his thing. And in most cases they’ll let the wife go in with him if he so desires.
Some clinics also allow for the sample to be produced at home if you live close to your clinic. Once the sample is produced, though, you need to keep it warm and get it to the clinic within 1 hour, or some of the sperm begin to die off.
Results
Generally you’ll get the results back within a couple of days of the SA, but it depends on your clinic. We got our SA results the following day.
Normal parameters of sperm are the following (*Based on World Heath Organization criteria, 1992. Table excerpted from Berger, G.S., Goldstein, M., and Fuerst, M. (1995). The Couple’s Guide to Fertility. New York: Doubleday):
Normal Ranges for a Semen Analysis*
Liquify?: Yes – within one hour
pH: 7.5 to 8.1
% Motility: Greater than or equal to 50%
% of 3-4 + Forward Motile Sperm: Greater than or equal to 50%
Sperm Concentration: 20-200 million per mL
Total Sperm Count: Greater than or equal to 40 million
Total Motile Sperm: Greater than or equal to 20 million per mL
White Blood Cells: Less than or equal to 1 million per mL
% Normal Morphology: Greater than or equal to 30%
Problems that might arise
There aren’t many problems that will present themselves in terms of the collection process, unless you miss the cup or can’t ejaculate.
If the results come back abnormal, your RE will suggest that you see a urologist, who can provide a further diagnosis. Additionally, at times, you can bypass sperm issues by trying IUI or even IVF with ICSI to get pregnant. I have also heard from my RE that there are other nifty high-tech sperm extraction procedures that can give you a chance of getting pregnant – even if your husband has a zero sperm count. At the same time, there will be men who will need to use donor insemination if this is your diagnoses.
Personal tips
Get one done as soon as possible! We didn’t get my husband’s SA done first because I had a lot of spotting and very irregular cycles; so we focused right away on diagnosing me. It wasn’t until we started thinking about treatments (3-4 months into the process) that my RE realized that he didn’t have a SA for my husband. I suppose I was trying to save him from the ‘embarrassment’ of doing one, but it ended up putting us back quite a few months, since his SA came back low.
Remember that counts wax and wane. My husband’s first SA came back pretty low – 20 million overall sperm, but 60% motility. The second one came back abysmally low – 4 million overall count and 20% motility. His third one was higher than the second, but lower than the first – 14 million overall sperm, and 50% motility. Chances are if you have a slightly low count one time, it might be normal another time. Or vice versa.
If the SA comes back abnormal, get thee to a urologist STAT! If there is a structural or hormonal problem, it can be treated. Your RE is NOT a male infertility specialist. For us – my husband had two varicoceles (varicose veins in the testicles) which needed to be surgically corrected. It took a couple of months to schedule the surgery, and since sperm take 90 days to be generated, it usually takes 3-6 months to see a result from that surgery. The sooner you see a specialist, the better.
Remember that there are some treatments for male factor. For us, our counts were so low we weren’t sure we were even a candidate for IUI – so we moved right on to IVF with ICSI. In the meantime, my husband got treatment for his varicoceles. It’s treatable, just takes a little time.
Keep a sense of humor about the collection part- the first one sucks, but it does get easier. I can’t tell you how many times we laugh about the rooms he’s been in for the process. Keeping a sense of humor about the whole thing really helps lighten it up and take the pressure off him a bit.
July 26, 2006 4 Comments
HSG (Hysterosalpingogram)
HSG (Hysterosalpingogram)
by Carolyn (otherwise known as the Heads Up Queen–not to be confused with the Heads Off Queen from Alice in Wonderland)
Why Would You be Having an HSG?
The HSG is one of the first diagnostic tests an RE runs when you’re having trouble conceiving. It is usually given shortly after the first infertility appointment, no later than CD 12 of your latest cycle.
Common problems that can be diagnosed with an HSG include: blocked fallopian tubes, uterine polyps, fibroids, and uterine defects such as a septum or a bicornate uterus.
What You Can Expect
The HSG is performed in the radiology department and is usually administered by a radiologist and an RE. You’ll lie down on the table underneath an x-ray machine, and the RE will insert a speculum as if you were having a PAP smear. The RE will then insert a catheter into your cervix and inject a clear dye into your uterus. For most women, this is the most uncomfortable part of the procedure. To me, the dye felt like sharp, strong menstrual cramps that lasted for a little over a minute. After that, I felt no pain at all.
While the RE is injecting the dye, the radiologist will take pictures of your uterus and tubes. Most of the time you should be able to see what’s happening on a screen somewhere in the room. You’ll be able to see the shape of your uterus, and if your tubes are clear you should be able to see each tube and then the dye as it spills out into your abdominal cavity.
If your tubes aren’t clear, the procedure may be more painful since the dye can’t spill out. The RE may try to force a closed tube open by injecting more dye, and this sometimes works.
After the test is over, you’ll be able to get dressed again and may go over your test results with the RE immediately. If not, your RE should schedule an appointment with you fairly soon to discuss the results. If your appointment isn’t for several days, try to get at least a preliminary report from the RE or radiologist while you’re still in the room.
Make sure to bring your own pad to the hospital or clinic because the dye is very messy and will be leaking out of you for several days. Dye that remains in the abdominal cavity is absorbed into the body. You may also experience some spotting after the procedure, but not heavier than a period.
There is some evidence that suggests that there is an uptick in fertility for the three cycles after the HSG.
Problems That Might Arise
Pain is the most common problem associated with the HSG. Some women experience only mild discomfort, while others experience severe pain. If you have a tight cervix the insertion of the catheter will be very uncomfortable. Occasionally, if you are experiencing severe pain your fallopian tubes may close even though they’re usually open.
If you are allergic to iodine, make sure you tell your RE before the procedure, since the most commonly used oil-based dye contains iodine and can cause an allergic reaction. There is also a water-based dye that can be used if you have an iodine allergy.
There is also a small chance of infection associated with the HSG, so your doctor should place you on antibiotics for several days before and after the procedure. If you feel more pain or experience heavy bleeding after the HSG, contact your doctor immediately.
Personal Tips
Since the HSG is usually the first invasive fertility procedure most women go through when they’re having trouble conceiving, it can be overwhelming and emotional. I did an acupuncture session the morning before my HSG, which was a wonderful way to stay calm and focused during the procedure.
Talk to your doctor before the HSG if you can. Ask them to tell you what they’re doing as they’re doing it, and don’t be afraid to tell them when something hurts. In my experience, REs seem to think that an HSG isn’t a very big deal. It’s a VERY big deal to the woman who is lying on the table, both physically and psychologically. Anything you can do to remind your doctor that this isn’t just “business as usual” for you will help.
July 26, 2006 374 Comments
Endometrial Biopsy
Endometrial Biopsy
by Carolyn
Why Would You be Doing an Endometrial Biopsy?
An endometrial biopsy is typically done when (not surprisingly) your doctor suspects you have a problem with your endometrium. Such problems can include endometrial hyperplasia, low estrogen or progesterone, and endometrial cancer. Blood tests are a more common (and less painful) way of detecting progesterone and estrogen problems. Endometrial hyperplasia and cancer are very rare in women under 40. Nonetheless, if you have problems with LP spotting and your progesterone levels are normal, an endometrial biopsy might be a good idea.
What You Can Expect
The biopsy is an outpatient procedure that only takes 10-15 minutes to complete. Before the biopsy you should take something for the pain, since the procedure isn’t performed under sedation. My doctor gave me the option to take 2 Percosets an hour beforehand. Two or three tablets of Motrin is an option if you don’t want to (or can’t) take something stronger.
The first stage of the biopsy is very similar to a normal PAP smear. After you get comfortable in the stirrups, your doctor will insert a speculum. If your cervix isn’t at the right angle, your doctor will need to use a tenaculum to move it into position. This does hurt, because the tenaculum has pincers that grip your cervix and usually cause some bleeding. After that, your doctor will dilate your cervix and insert a Pipelle aspirator, which uses suction to collect the sample. You’ll feel cramping and then a pulling as the aspirator gathers its sample. If you’ve had an HSG, this part of the biopsy will feel very familiar.
After the doctor has collected a large enough sample, he/she will remove the instruments, and you’re done! If the doctor needed to use a tenaculum, they will probably use some silver nitrate to stop the bleeding on your cervix.
Post-biopsy, you may have some cramping and tenderness, and your doctor will probably recommend that you take more pain medication that night. For what it’s worth, I felt absolutely no pain after getting home and didn’t need to take more painkillers. You’ll probably experience some spotting, possibly as heavy as a period. If you start bleeding more than that, or the bleeding lasts longer than a day or two, call your doctor.
Lab results should be available within a week. Before you leave, ask your doctor when you can schedule a follow-up appointment to discuss them.
Problems That Might Arise
The main problems you can encounter when doing an endometrial biopsy are pain and bleeding after the procedure. For the pain, my doctor recommended Motrin, but also gave me two extra Percosets just in case I needed them.
If you experience heavy bleeding (heavier than your period) or the bleeding continues for more than a day or two, call your doctor. It’s unusual, but it does happen. Also, try to refrain from any strenuous physical activity for a few days after the procedure. See below for my personal story about why this is a good idea.
Personal Tips
Anything you can do to relax while you’re on the table will help make the procedure less uncomfortable. I did deep breathing exercises until after the sample had been collected. DEFINITELY take some kind of pain medication beforehand.
One of the things I really appreciated before the biopsy started was having my doctor explain to me which instruments she would be using and why. She also told me what she was going to do before she used each instrument. If your doctor doesn’t take a minute to walk you through the procedure before starting it, I recommend that you ask them to do so. Relaxing was much easier when I knew what she was doing and why.
Take it easy for a few days after the procedure. You don’t have to go on bedrest or anything, but try to refrain from any strenuous physical activity. I made the mistake of hauling some heavy things up and down stairs the day after my biopsy and spent the following day regretting it from the couch because it felt like someone had kicked me in the gut every time I moved. Be ye not so stupid.
As a final note, if you take Percoset or other narcotic painkiller beforehand, be sure to have someone at the clinic with you to drive you home. Not only can these painkillers impair your ability to operate a car, but they can also make you extremely nauseated. Let’s face it, no one wants to drive when all they really want to do is throw up.
July 26, 2006 719 Comments
Laparoscopic Surgery When Endometriosis is Suspected
By Royalyne
Why would you be having laparoscopic surgery?
Laparoscopic surgery (often referred to as “lap”) is the only real way to diagnose endometriosis. Your gynecologist or even family doctor may have made an assumptive diagnoses based on your symptoms, but a true diagnoses can only be made when the endometrial adhesions are seen. The description of the surgery (-scopic) suggests that the doctor intends to merely look and see if adhesions are present, but once adhesions are found they are removed during the same procedure. Endometrial adhesions are most frequently found on the ovaries and fallopian tubes, but may be present anywhere in the abdomen. Endometriosis on the ovaries can form cysts, called endometrioma.
What you can expect
You will need somebody with you, whom must remain at the hospital throughout your procedure to drive you home.
Each hospital will have its own standard operating procedures (SOP), I can only write from my experience, using the SOP of my hospital. Your lap will be performed in a hospital by a gynecologist as an outpatient surgery. You will be placed under general anesthesia for the procedure. You will be asked to follow their standard pre-op procedures, such as fasting the night before. Beforehand you will have an IV started and provide a urine sample for a pregnancy test. The doctor will brief you on his/her plan for the surgery and what will be done if adhesions are found. The anesthesiologist will also speak to you about the anesthesia that will be used and the endotracheal tube (the breathing tube they put in). A few minutes prior to being moved to the operating room you will be given a shot of a medication in the category benzodiazepines, most likely midazolam (brand name- Versed). This medication is a relaxant and also an amnesic (reduces your memory of events while on the medication). You may begin to feel drowsy and “stoned,” which is normal for this medication. Once you are in the operating room and transferred to the operating table, additional medications will be administered and once you are completely unconscious a breathing tube will be placed in your throat.
A small incision is made in your abdomen to facilitate the insertion of the laparoscope. There is a camera on the laparoscope that allows the doctor to see your internal organs without making a large incision. Another incision, this one much smaller, is made to allow a tube to be inserted. Sterile air is pushed through this tube into your abdomen. Once your abdomen is inflated, the doctor can see the entire area much easier and access areas that would have otherwise been blocked from view. The doctor will basically look around for anything out of the ordinary. Endometrial lesions and endometrioma will be removed with a laser, but also shifted ovaries can be returned to the correct position and anchored, and likely many other beneficial procedures. The doctor will take many pictures, both before and after shots, for your patient file.
Once the surgery is complete, the air is released and your abdomen deflates. The incisions are sealed externally with glue, probably stitches internally, but for the life of me I can’t remember what they said (that darn Versed). The breathing tube is removed and a medication is administered to slightly reverse the affects of the anesthesia. You will be moved to the recovery area until you become more fully conscious, and then returned to the outpatient area that you started in. The doctor will then come speak to you about the surgery: what was found, what was done to treat it, your prognosis, etc. You will be given a prescription for painkillers, and if you are in pain (anesthesia is very much different from painkillers) you will be given a dose of the medication prescribed. Once you are able to sit up and feel ready to leave, you will be taken by wheelchair to the car.
You will be under restrictions for 2 weeks following your surgery. Abdominal surgery requires cutting abdominal muscles, and the abdomen is your core, it is used when moving almost any part of your body. The restrictions are in your best interests, and in the best interests of your healing body.
Problems that may arise and ways to troubleshoot
You may notice pain or cramping in your neck, shoulders, or upper arms for a few days following surgery. This pain is a result of the trapped air from the inflation of your abdomen. Some air gets trapped and is not released when your abdomen deflates. This air “floats” in your body, moving to the highest part of your body. Lying as flat as possible, or with your legs elevated will disperse this trapped air, spreading it out and not allowing it to concentrate in one area. The air is gradually absorbed into your blood stream and released within a few days. A way to encourage that absorption is a heating pad and/or massage. When the area has a greater blood flow the trapped air is absorbed faster.
As with all surgeries, your incisions are very important. If they become more painful, red, swollen, or begin producing a discharge, see your doctor immediately.
My personal tips
My procedure took an incredibly long time due to the amount of adhesions I had and where they were located (one ovary was ripped from its proper location with an endometrioma, minor adhesions on the bladder, lots of adhesions everywhere), but was not difficult at all. When I was awake, though, I did notice an odd taste in my mouth (from the breathing tube) and my mouth felt incredibly dry. Be sure to have a nice cool bottle of water nearby once you get home (or for the drive if it’ll last longer than 10-15 minutes).
The person who drives you should be somebody you trust enough to have with you when the doctor comes to give you the post-op report. You will likely be very groggy (I don’t remember seeing my doctor afterwards, but I’m told he was around for 10-15 minutes telling my husband about everything). This person should also be taking notes, because you will want every detail and their memory may not be perfect enough for your liking if they don’t write it all down.
The trapped air was my biggest complaint afterwards, and the painkillers I got (darvocet) did nothing for that pain. Apparently the main use of darvocet is for incision pain, of which I had almost none. Needing darvocet was my downfall, but I’m allergic to vicodin (apparently their drug of choice post-surgery). I ended up taking either Tylenol or Advil liquigels for the air bubble pain, whichever was closest to the couch. My husband was nice enough to give me twice-daily shoulder rubs and keep my microwavable heat pad nice and warm for me. The pain lasted 3 days, including the day of surgery, but after the second day it was more like the pain of an overworked muscle.
My main incision was less than an inch long, inside the bottom of my belly button. It felt like a cat scratch, and within a week I didn’t feel anything at all. The second incision was un-located for 2 entire days, as it was located below the pubic hair line and caused absolutely no discomfort. The only time I had any pain in my main incision was during the process of changing positions (i.e. sitting to standing and its inverse, rolling over, etc.).
Don’t wear a belt for a while, especially one with a big, cute buckle. Pressure on that navel incision is not a good idea; it hurts. All of my pants are low-rise, but sitting down or bending over with a belt on pushes the buckle right into that incision.
Restrictions exist for a reason. You use your stomach to wiggle your toes and pick up your head off the pillow, and just about everything else. The 20lb lifting restriction extends to the vacuum cleaner, even if you’re just pushing and pulling it across the carpet. Take advantage of your restrictions, they really are in your best interests. I was back to basically my normal routine about
4-5 days after my surgery, except for strictly following the restrictions. Once my restrictions were lifted I had no problem going back to that routine, including shoveling 2 feet of snow in my driveway. You know your body best, you know how slowly to ease into things once the restrictions are lifted. But don’t rush the restrictions, they were put in place by somebody who has seen your insides, and if you trust them enough to let them cut you open you need to trust their judgment on restrictions as well.
July 26, 2006 110 Comments










